

- About Us
- Information
-

The Author ensures that the research has been conducted responsibly and ethically with adherence to all relevant regulations. read more..
- For Authors
- For Reviewer
- Manuscript Guidelines
- Membership
- Publication Ethics
-
- Journals
- Reprints
- e-Books
- Videos
- Policies
- Contact Us
 COVID-19
- Submissions



Full Text
Gerontology & Geriatrics Studies
AI-Driven Digital Health Perspectives on Occupational Exposure to Cement and Associated Biological Effects in Construction Workforces
Mahin Jamil1, Adnan Anwar2, Jaffar Waqas3, Zeenat Khan4*, Haroon Imtiaz5 and Daud Khan6
1 Department of Civil Engineering, University of Engineering and Technology (UET), Pakistan
2 Civil Automation Engineer, Al Shahbaz Enterprises, Pakistan
3 Institute of Geo-Information and Earth Observation, Pir Mehr Ali Shah Arid Agriculture University, Pakistan
4 Research Analyst, Al-Mussawir Engineers, Pakistan
5 Department of Civil Engineering, Capital University of Science & Technology, Pakistan
6 Resident Engineer, Al-Mussawir Engineers, Pakistan
*Corresponding author:Zeenat Khan, Research Analyst, Al-Mussawir Engineers, Rawalpindi, Pakistan
Submission: June 26, 2026; Published: August 31, 2026

ISSN 2578-0093Volume10 Issue 3
Abstract
Cement is an essential construction material but also represents a significant occupational health hazard due to its highly alkaline nature and the presence of toxic trace metals such as hexavalent chromium, nickel, and cobalt. Prolonged exposure through skin contact, inhalation, or accidental ingestion can result in dermatological disorders including irritant and allergic contact dermatitis, chemical burns, and chronic eczema, as well as systemic effects characterized by oxidative stress, inflammation, and liver and kidney dysfunction. Recent evidence suggests that molecular regulators such as Sirtuin 1 (SIRT1) may play an important role in mediating cement-induced cellular damage and inflammatory responses. Advances in Artificial Intelligence (AI) offer new opportunities for occupational health monitoring through real-time exposure assessment, machine learning-based disease prediction, computer vision-assisted dermatological screening, and biomarker analysis. This review summarizes the chemical composition of cement, its dermatological and biochemical effects, underlying toxicological mechanisms, and the emerging role of AI in improving occupational health surveillance. The integration of AI with occupational toxicology may facilitate early disease detection, personalized risk assessment, and enhanced worker protection in construction environments.
Keywords:Cement dust; Occupational toxicity; Dermatitis; SIRT1 and Artificial intelligence
Abbreviations: SIRT1: Sirtuin 1; AI: Artificial Intelligence; AST: Aspartate Aminotransferase; ALT: Alanine Aminotransferase; ALP: Alkaline Phosphatase; SOD: Superoxide Dismutase; CAT: Catalase; ROS: Reactive Oxygen Species; ANN: Artificial Neural Network; CNNs: Convolutional Neural Networks
Highlights
1. Cement exposure causes dermatological, biochemical, and systemic health effects in construction workers.
2. Hexavalent chromium and other heavy metals promote oxidative stress and inflammatory responses.
3. SIRT1 may serve as a potential biomarker of cement-induced cellular toxicity.
4. Artificial Intelligence supports exposure assessment, disease prediction, and health surveillance.
5. AI-integrated occupational health systems can improve worker safety and preventive interventions.
Introduction
Cement is an indispensable material in modern construction; however, its physicochemical characteristics present considerable occupational health challenges for workers involved in its handling and application. The material consists primarily of calcium, silicon, aluminum, iron, and magnesium oxides, together with smaller quantities of sulfur compounds, alkali oxides, and various trace metals [1]. During hydration, cement undergoes chemical reactions that generate calcium hydroxide and create a strongly alkaline environment capable of damaging biological tissues upon direct contact [2]. Furthermore, the presence of trace elements such as chromium, nickel, cobalt, selenium, thallium and lead increases the potential for toxicological and immunological effects among exposed individuals [3]. Repeated contact with wet cement, particularly in the absence of appropriate personal protective equipment, can result in a range of adverse health outcomes including skin irritation, allergic reactions, chemical burns, and chronic inflammatory conditions [4]. The combined effects of alkalinity, abrasive particles, and toxic metal constituents establish cement as an important occupational hazard requiring effective risk management and preventive interventions within the construction sector [5].
Among the various occupational health concerns associated with cement, dermatological disorders remain one of the most frequently reported consequences of exposure. Construction workers routinely encounter cement during activities such as mixing, transporting, pouring, and finishing concrete, resulting in prolonged skin contact with both wet cement and cement dust [6]. The highly alkaline nature of hydrated cement, together with the abrasive action of particulate materials and the presence of sensitizing metals, contributes significantly to the development of skin damage and inflammatory responses [7]. Occupational exposure has been associated with a broad spectrum of dermatological manifestations, including dryness, erythema, scaling, fissuring, irritant contact dermatitis, allergic contact dermatitis, and chronic eczema [8]. Continuous exposure may progressively compromise the epidermal barrier, facilitate penetration of irritants and allergens while increase susceptibility to secondary infections and persistent inflammatory conditions [9]. Consequently, cement-related skin diseases continue to represent a major occupational health burden that can negatively affect worker productivity, quality of life, and long-term well-being [10].
In addition to dermatological effects, growing evidence indicates that cement exposure may induce significant biochemical and cellular alterations throughout the body. Cement dust contains respirable particulate matter and potentially hazardous elements including chromium, cadmium, lead, nickel, and cobalt, which may enter the body through inhalation, ingestion, or dermal absorption pathways [11]. Following absorption, these substances can accumulate in various tissues and interfere with normal physiological and metabolic processes [12]. Numerous toxicological investigations have demonstrated that chronic exposure to cement dust promotes oxidative stress through excessive generation of reactive oxygen species and disruption of endogenous antioxidant defense mechanisms [13]. Such disturbances have been associated with increased lipid peroxidation, inflammatory activation, hepatic dysfunction, renal impairment, and cellular injury [14]. Moreover, certain heavy metals present in cement possess immunotoxic, genotoxic, and potentially carcinogenic properties that may contribute to long-term adverse health outcomes among exposed workers [15]. These findings emphasize the systemic nature of cement-related toxicity and highlight the importance of comprehensive occupational health monitoring strategies [16].
The widespread use of cement worldwide and the substantial number of workers involved in construction activities make cement exposure an important public health concern. Epidemiological studies have consistently reported elevated rates of occupational skin disorders and exposure-related health complications among construction workers, particularly in environments where preventive measures are inadequate [17]. Although personal protective equipment, workplace hygiene practices, engineering controls, and routine medical surveillance have demonstrated effectiveness in reducing occupational risks, implementation and compliance remain inconsistent across many regions and industries [18]. Conventional occupational health surveillance programs frequently depend on periodic assessments that may not detect early physiological or molecular alterations associated with chronic exposure [19]. As a result, there is increasing interest in developing innovative approaches capable of providing continuous monitoring and early identification of exposure-related health effects [20].
Recent advances in Artificial Intelligence (AI) have introduced new opportunities for transforming occupational health surveillance and risk management. Technologies such as machine learning, computer vision, wearable sensing systems, and biomarker-based analytics enable the collection, integration, and interpretation of large volumes of environmental, clinical, and molecular data [21]. These intelligent systems can support realtime exposure assessment, automated dermatological screening, predictive disease modeling, and personalized health risk evaluation among workers exposed to occupational hazards [22]. AI-driven approaches have also shown considerable potential for identifying subtle biological changes before the onset of clinically detectable disease, thereby facilitating timely preventive interventions and improving workplace safety outcomes [23]. Furthermore, the integration of AI with molecular toxicology research has generated interest in biomarkers such as Sirtuin 1 (SIRT1), which may provide mechanistic insights into oxidative stress, inflammation, and cellular aging associated with cement exposure [24]. Therefore, the convergence of occupational toxicology, biomarker science, and artificial intelligence offers a promising framework for advancing precision occupational health and improving the protection of construction workers exposed to cement-related hazards [25,26].
Chemical Constituents of Cement and Their Dermatological Implications
Cement is a heterogeneous inorganic material extensively utilized in construction activities and is composed of a diverse mixture of mineral oxides and trace constituents that may adversely affect human health following occupational exposure [23]. The major chemical components of cement include calcium oxide, silicon dioxide, aluminum oxide, ferric oxide, and magnesium oxide, which are essential for the development of its hydraulic and binding characteristics (Table 1) [24]. During construction operations, the addition of water initiates a series of hydration reactions that transform these mineral phases into hydration products responsible for strength development and setting behavior [25]. One of the principal by-products of these reactions is calcium hydroxide, which creates a highly alkaline environment with the potential to damage biological tissues upon direct contact [26]. Exposure of the skin to wet cement can disrupt the integrity of the epidermal lipid barrier, resulting in excessive moisture loss, irritation, and progressive skin dryness [27]. Besides the major oxides, cement contains varying concentrations of trace metals and impurities, including chromium, nickel, cobalt, selenium, thallium, and lead [28]. These elements originate from natural raw materials such as limestone, clay, and shale or may be introduced during clinker production and manufacturing processes [29].
The presence of these potentially toxic substances increases the likelihood of adverse interactions with biological systems and contributes to the hazardous nature of cement exposure [30]. Construction workers are routinely exposed to these chemical constituents during activities such as concrete mixing, placement, finishing, and handling of cement-based materials, creating multiple opportunities for direct dermal contact [31]. The risk of exposure is particularly elevated when appropriate personal protective equipment, including gloves and protective clothing, is not consistently used [32]. Repeated and prolonged contact with cement can progressively compromise epidermal integrity, facilitating deeper penetration of harmful substances through the skin barrier [33]. Consequently, the complex chemical profile of cement constitutes an important occupational health concern and is associated with a range of acute and chronic dermatological effects among construction workers [34,35].
The dermatological consequences of cement exposure arise from a combination of chemical, (Table 1) physical, and immunological mechanisms that affect the structure and function of the skin [36]. Owing to its strongly alkaline nature, wet cement can induce irritant contact dermatitis when exposure is prolonged, particularly when cement remains trapped beneath clothing, gloves, footwear, or other protective materials for extended periods [37]. In addition to chemical irritation, the abrasive characteristics of sand and particulate matter present in cement mixtures can mechanically damage the epidermis, thereby increase skin permeability and enhance the penetration of reactive compounds into deeper tissue layers [38]. Among the trace constituents, hexavalent chromium is regarded as one of the most significant sensitizing agents and has been strongly implicated in the development of allergic contact dermatitis among exposed workers [39]. Recurrent exposure to chromium-containing cement may induce immunological sensitization, resulting in chronic inflammatory reactions characterized by itching, erythema, edema, and scaling of affected skin regions [40].
Table 1:Typical chemical constituents and compositional range of Portland cement with their functional significance in construction materials [24,35].
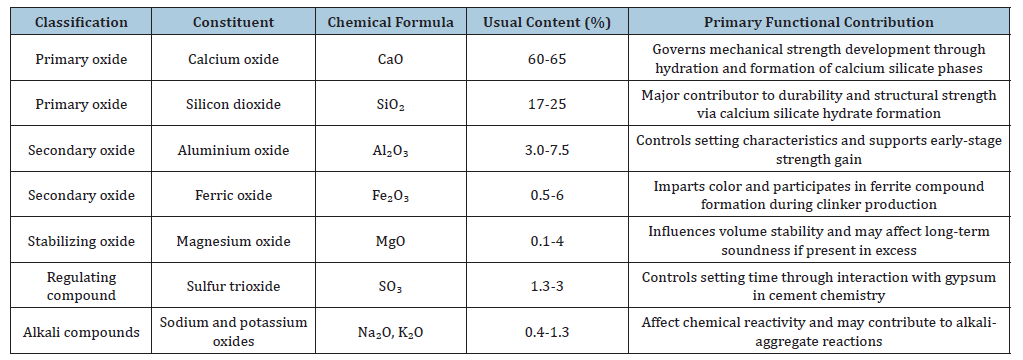
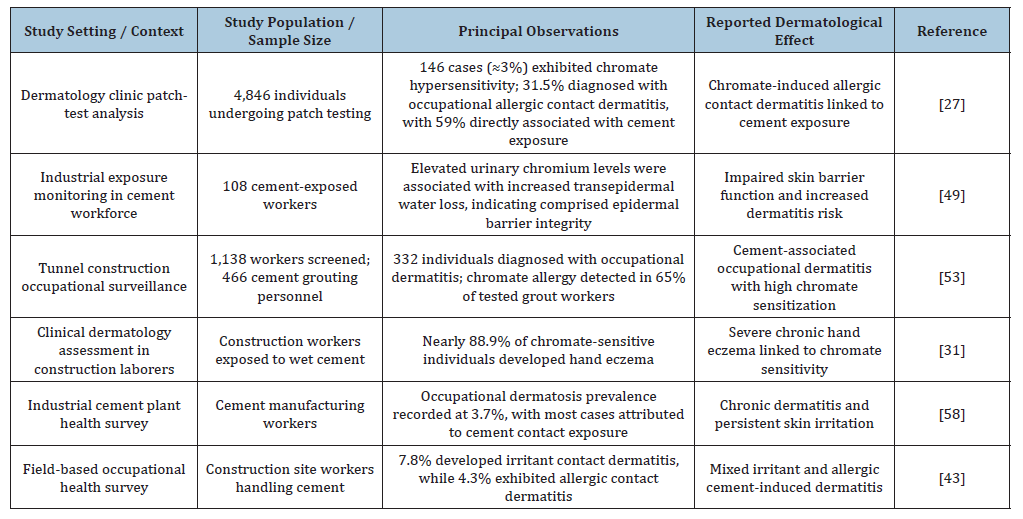
Other metallic elements, including cobalt and nickel, have likewise been associated with hypersensitivity reactions and the development of persistent eczematous conditions in susceptible individuals [41]. Workers who handle cement on a regular basis without adequate skin protection commonly report symptoms such as dryness, pruritus, fissuring, erythema, and irritation, particularly affecting the hands, wrists, and forearms [42]. Under severe exposure conditions, the corrosive action of highly alkaline cement may cause chemical burns capable of penetrating deep tissue layers and producing ulceration, tissue necrosis, or permanent scarring [43]. Furthermore, the retention and accumulation of heavy metals within skin tissues may contribute to long-term dermatological abnormalities and may also trigger systemic inflammatory responses [44]. Continued exposure to these harmful constituents can impair normal skin repair processes, compromise regenerative capacity, and increase vulnerability to opportunistic bacterial or fungal infections [45]. As a result, cement-related skin disorders remain among the most significant occupational health concerns affecting workers in the construction industry (Table 2).
Table 2:Reported evidence on dermatological outcomes associated with occupational cement exposure.
Dermatological Manifestations Associated with Cement Exposure
Skin-related disorders are among the most commonly documented occupational illnesses in individuals working within the construction and cement-handling sectors [46]. Continuous occupational contact with cement, particularly in its wet state, exposes workers to strongly alkaline substances, abrasive particulates, and allergenic metal compounds that collectively compromise skin integrity and initiate inflammatory processes [47]. Routine construction activities such as mixing, transporting, pouring, and finishing concrete often involve unavoidable direct skin exposure, especially in environments where personal protective equipment is inconsistently used or unavailable [48].
The multifactorial chemical composition of cement, including calcium oxide, silica-based compounds, aluminum derivatives, and trace metals such as chromium and cobalt, plays a key role in triggering diverse skin reactions [49]. These dermatological responses may vary in severity, ranging from mild irritation and xerosis to severe inflammatory dermatitis and chemically induced burns [50]. Anatomical regions such as the hands, forearms, and lower extremities are most frequently affected due to their direct and repeated exposure during manual labor tasks [51]. Consequently, individuals employed in cement production facilities, transportation systems, and construction sites face an elevated risk of developing occupational skin diseases linked to cement exposure [52].
The intensity and frequency of cement-induced dermatological conditions are influenced by multiple determinants, including exposure duration, concentration of irritant and sensitizing agents, environmental conditions such as humidity and temperature, and individual biological susceptibility [53]. Sustained contact with wet cement progressively weakens the epidermal barrier, thereby increasing skin permeability and enhancing susceptibility to both irritant and allergic reactions [54]. Moreover, the presence of coarse particulate matter within cement mixtures can cause repeated micro-injuries to the skin surface, which facilitates deeper penetration of harmful chemical constituents [55].
Evidence from occupational health investigations indicates that irritant contact dermatitis, allergic contact dermatitis, and chemical burns represent the most prevalent dermatological conditions among exposed workers [56]. With ongoing exposure, individuals may also develop chronic dermatological complications such as skin fissuring, hyperkeratosis, and secondary microbial infections [57]. Collectively, empirical findings from occupational studies highlight that cement-related skin disorders are not only widespread but also have significant implications for worker productivity, occupational efficiency, and overall quality of life [58]. A summary of selected epidemiological and surveillance studies reporting dermatological outcomes in cement-exposed populations is presented in Table 2 [59].
Irritant Contact Dermatitis Induced by Cement Exposure
Irritant contact dermatitis is among the most frequently encountered occupational skin conditions in workers exposed to cement in construction-related environments [60]. This condition is primarily driven by the strongly alkaline nature of wet cement, which may reach pH values close to 12 during hydration processes [61]. Such extreme alkalinity disrupts the epidermal lipid layer, leading to direct chemical injury of the outer skin surface [62]. Workers are commonly exposed during activities such as mixing, transporting, and applying cement-based materials, where repeated or prolonged contact allows alkaline substances to penetrate the skin barrier [63]. This penetration initiates an inflammatory response characterized by erythema, dryness, pruritus, and burning sensations [64]. The presence of abrasive sand and particulate matter within cement further exacerbates skin damage by causing micro-abrasions that increase permeability to chemical irritants [65]. In occupational settings where protective measures are inadequate, irritant dermatitis typically develops progressively following repeated exposure to cement [66]. Environmental factors such as humidity, perspiration, and extended working hours further intensify the severity of skin irritation [67].
The clinical progression of irritant contact dermatitis often begins with mild cutaneous symptoms but may advance to more severe pathological changes with continued exposure [68]. Early manifestations generally include dryness and erythema, which may progress to scaling, fissuring, and heightened skin sensitivity in affected areas [69]. Persistent exposure to alkaline cement compounds gradually impairs epidermal integrity and increases transepidermal water loss, reflecting compromised barrier function [70]. Occupational studies have reported that cementexposed workers frequently exhibit reduced skin barrier resilience, predisposing them to recurrent irritation and inflammatory episodes [71]. The hands represent the most commonly affected anatomical site due to their direct involvement in cement handling activities [72]. Beyond physical discomfort, chronic irritant dermatitis can significantly impair manual dexterity and reduce the ability to perform routine occupational tasks efficiently [73]. Secondary microbial infections may occur when skin fissures provide entry points for pathogens into deeper tissues [74]. In the absence of adequate preventive measures and timely treatment, irritant contact dermatitis may progress into chronic and persistent dermatological conditions [75]. These findings highlight the critical importance of implementing preventive strategies, including appropriate protective gloves, improved occupational hygiene practices, and worker education regarding cement-related skin hazards [76].
Allergic Contact Dermatitis Triggered by Cement Exposure
Allergic contact dermatitis related to cement exposure is primarily attributed to sensitization caused by hexavalent chromium compounds present within cement materials [77]. Chromium is recognized as one of the most potent occupational allergens, capable of inducing strong immune-mediated hypersensitivity reactions following repeated skin exposure [78]. In contrast to irritant dermatitis, which arises from direct chemical damage to the skin, allergic contact dermatitis develops when chromium ions penetrate the epidermal barrier and trigger a delayed immune response in sensitized individuals [79]. Once sensitization has been established, even minimal exposure to chromium-containing cement can provoke pronounced inflammatory reactions [80]. Workers who handle cement without adequate protective gloves or clothing are at particularly high risk, as wet cement facilitates the solubilization and dermal penetration of chromium compounds [81]. Clinical manifestations typically include pruritus, erythema, edema, and eczema-like lesions, most commonly affecting exposed areas such as the hands and forearms [82]. Occupational health studies indicate that chromate sensitivity constitutes a significant proportion of cement-related allergic skin disorders among construction workers [83].
The long-term impact of allergic contact dermatitis is often considerable, as sensitization to chromium tends to persist even after exposure has been minimized or eliminated [84]. Once immunological sensitization occurs, affected individuals may experience recurrent eczematous flare-ups upon re-exposure to chromium-containing materials [85]. This chronic hypersensitivity is characterized by persistent itching, inflammation, and scaling, which may significantly impair skin health and function over time [86]. In severe cases, individuals may be compelled to change occupational roles or completely avoid tasks involving cement exposure due to the intensity of symptoms [87]. Nevertheless, clinical symptoms may continue to occur because of residual sensitization or inadvertent exposure to chromium present in other environmental or industrial sources [88]. Such persistent allergic reactions can substantially reduce quality of life, leading to discomfort, sleep disturbances, and decreased occupational productivity [89]. Furthermore, co-sensitization to other metals such as cobalt has been documented among cement-exposed workers, thereby increasing the complexity of clinical management [46]. Preventive approaches, including the reduction of hexavalent chromium content in cement through chemical modification techniques, have been introduced in certain regions to reduce the incidence of sensitization and improve occupational safety [47].
Cement-Induced Chemical Burns and Cutaneous Ulceration
Cement burns represent severe occupational skin injuries that arise when wet cement remains in prolonged contact with the skin, leading to progressive chemical damage driven by its highly alkaline composition [48]. During the hydration process, cement generates calcium hydroxide, which establishes a strongly alkaline environment capable of chemically corroding skin tissues upon sustained exposure [49]. Workers engaged in activities such as kneeling in fresh concrete, handling cement mixtures, or wearing cement-soaked clothing are particularly vulnerable to these injuries due to prolonged dermal contact [50]. Unlike thermal burns, cement-induced burns often develop insidiously and may not produce immediate pain, resulting in delayed recognition and continued exposure [51]. Early clinical manifestations typically include mild erythema, irritation, and a delayed burning sensation that may emerge several hours after contact [52].
With ongoing exposure, alkaline substances progressively penetrate deeper layers of the skin, leading to escalating tissue destruction and structural damage [53]. The abrasive nature of cement mixtures, which often contain sand and other particulate matter, further exacerbates injury by disrupting the skin surface and facilitating deeper chemical penetration [54]. Consequently, the condition may advance from superficial irritation to more severe tissue breakdown and ulcer formation [55]. Cement burns therefore constitute a significant occupational hazard for construction workers who are routinely exposed to wet concrete during daily work activities [56]. The severity of injury increases when exposure is not promptly identified or when decontamination is delayed, allowing continued chemical action on the skin [57]. Within a few hours of exposure, affected areas may develop blistering, swelling, and intense pain as tissue injury progresses [58]. In more advanced cases, chemical corrosion may extend into deeper dermal and subdermal layers, resulting in partial-thickness or full-thickness burns [59]. Such injuries frequently require medical intervention and may lead to long-term consequences including permanent scarring, functional impairment, or loss of normal skin integrity [60].
Chronic Dermatological Disorders in Cement- Exposed Construction Workers
Long-term occupational exposure to cement and associated construction materials is strongly linked with the development of chronic dermatological disorders among construction workers [61]. Continuous interaction with cement dust and wet cement progressively compromises the integrity of the skin barrier, thereby reducing its natural protective and regenerative capacity [62]. Consequently, affected workers commonly present with persistent dryness, scaling, and progressive thickening of the skin following repeated exposure [63]. These manifestations are most frequently observed on the hands and fingers, as these anatomical sites are directly involved in manual construction activities [64]. Ongoing irritation of the skin may induce excessive keratin formation, leading to hyperkeratosis characterized by hardened, thickened, and less flexible skin surfaces [65]. Although this adaptive response may initially serve a protective function, it often results in painful fissuring and cracking that can hinder routine occupational tasks [66]. In addition, repeated exposure to cement dust contributes to the removal of natural lipids from the skin surface, resulting in dryness, rough texture, and reduced skin elasticity [67].
With continued exposure over time, these dermatological alterations may evolve into persistent and long-standing skin conditions that persist even after acute inflammatory episodes have resolved [68]. Evidence from occupational health studies, as summarized in Table 2, indicates that workers in construction environments frequently experience chronic skin complaints affecting primarily the upper limbs [69]. These findings highlight the cumulative and progressive nature of cement-related skin damage in occupational settings [70]. Chronic dermatological conditions can significantly impair both physical well-being and occupational efficiency among affected workers [71]. Persistent skin dryness and fissuring create entry points for microbial pathogens, thereby increasing the risk of secondary bacterial and fungal infections [72]. Such infections may further aggravate inflammation and delay the healing process of damaged skin [73]. In some cases, ongoing irritation and sensitization may lead to chronic eczema and other persistent inflammatory skin diseases [74].
Inadequate workplace hygiene practices and inconsistent use of protective equipment further intensify the severity and frequency of these conditions [75]. Workers employed in cement production facilities, transportation systems, and construction sites remain continuously exposed to these risks throughout their working life [76]. The cumulative burden of exposure often results in worsening symptoms with increasing duration of employment in the construction sector [77]. These chronic skin disorders can also impair manual dexterity, reduce productivity, and contribute to increased absenteeism from work [78]. Therefore, strengthening occupational health strategies, improving protective measures, and enhancing worker awareness are essential to reduce the burden of chronic cement-related skin diseases in the construction industry [79]. Ultimately, chronic dermatological conditions associated with cement exposure represent a major and persistent occupational health challenge [80].
Biochemical and Cellular Impacts of Cement Exposure
Cement dust exposure is increasingly recognized as a major occupational health concern due to its chemically heterogeneous nature and its ability to induce widespread biochemical disruptions (Figure 1) [63]. The particulate matter of cement contains numerous toxic constituents, including silicon oxide, aluminum oxide, iron oxide, chromium, lead, cadmium, nickel, cobalt, arsenic, sodium, potassium, sulfur, and magnesium compounds [60]. These components behave as environmental xenobiotics that may interact with biological systems following inhalation, ingestion, or dermal absorption [68]. After inhalation, fine particles can become lodged in the respiratory tract and subsequently transported via mucociliary clearance to the gastrointestinal system, where systemic absorption may occur [61]. Once internalized, these toxic elements can accumulate in vital organs such as the liver, kidneys, lungs, and gastrointestinal tissues [80]. Such bioaccumulation disrupts normal cellular processes and contributes to structural and functional impairment across multiple organ systems [66]. Toxicological evidence links these processes to oxidative damage, cellular dysfunction, and inflammatory reactions that collectively contribute to respiratory, hepatic, and gastrointestinal diseases [72].
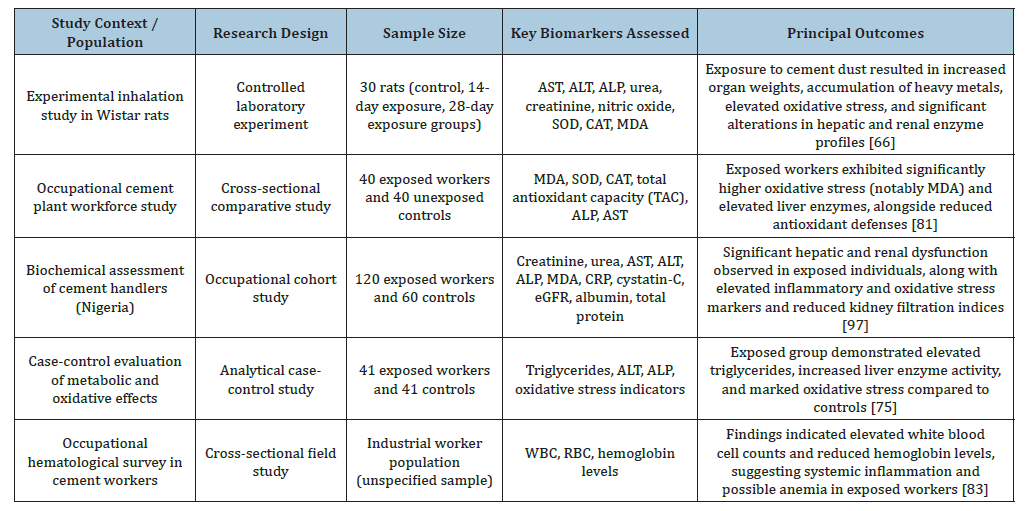
Experimental and epidemiological investigations have consistently demonstrated that cement dust exposure induces a wide range of biochemical alterations (Table 3) [64]. Elevated serum levels of liver enzymes, including aspartate aminotransferase (AST), alanine aminotransferase (ALT), and alkaline phosphatase (ALP), have been reported, indicating hepatic injury [81]. Similarly, increased concentrations of creatinine and urea suggest compromised renal function in exposed individuals [71]. These biochemical disturbances are frequently accompanied by enhanced lipid peroxidation and reduced activity of antioxidant enzymes such as superoxide dismutase (SOD) and catalase (CAT), reflecting oxidative imbalance at the cellular level [62]. Additionally, raised levels of inflammatory mediators such as C-reactive protein and nitric oxide indicate activation of systemic inflammatory pathways [82]. Collectively, these findings confirm that prolonged exposure to cement dust disrupts cellular homeostasis and contributes to progressive biochemical and molecular dysfunction [74].
Figure 1: Dust generation throughout the different phases of cement manufacturing [57].
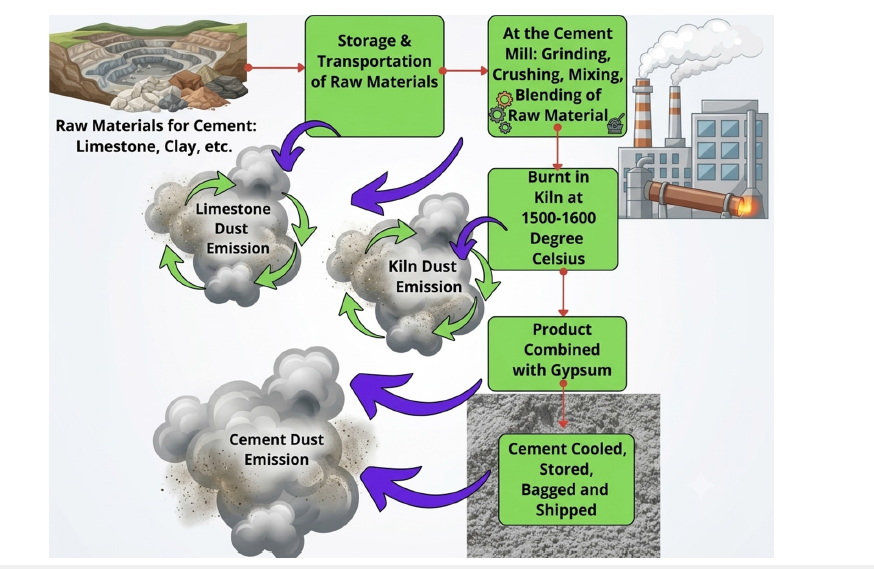
Table 3:Selected case investigations on biochemical and cellular alterations associated with cement dust exposure
Compromise of Skin Barrier Integrity
Cement exposure exerts a profound detrimental effect on the structural and functional integrity of the skin barrier due to its strongly alkaline composition and abrasive particulate content [69]. Wet cement typically exhibits a pH exceeding 12, which is sufficient to disrupt the lipid matrix of the epidermis [83]. The stratum corneum, which serves as the primary protective barrier regulating water retention and preventing pathogen entry, becomes compromised under such conditions [70]. Prolonged exposure to cement results in dissolution of epidermal lipids and denaturation of structural proteins, leading to barrier dysfunction [84]. This increases skin permeability to irritants, allergens, and toxic substances [60]. Mechanical abrasion caused by silica and sand particles further intensifies epidermal damage by producing micro-injuries that facilitate deeper chemical penetration [85]. Consequently, exposed workers frequently present with dryness, erythema, itching, and desquamation [75].
Chronic exposure progressively deteriorates epidermal integrity, leading to long-term dermatological complications [86]. Increased transepidermal water loss results in persistent dehydration and reduced elasticity of the skin [77]. In severe cases, fissuring, ulceration, and inflammatory lesions may develop, significantly impairing normal skin function [87]. Occupational surveys consistently report a high incidence of dermatitis, eczema, and skin irritation among cement workers and construction laborers [79]. The presence of heavy metals such as chromium further exacerbates these effects by promoting allergic sensitization [88]. Sustained barrier disruption also increases vulnerability to microbial invasion and secondary infections [80]. These findings underscore the necessity of preventive interventions, including protective clothing, gloves, and strict hygiene practices to minimize dermal exposure in occupational environments [89].
Oxidative Stress and Inflammatory Mechanisms
Cement dust exposure has been strongly associated with the induction of oxidative stress through excessive production of reactive oxygen species (ROS) [81]. Fine particulate matter can penetrate deep into the respiratory system and enter systemic circulation, where it interacts with cellular structures [90]. Within biological tissues, toxic metals and particles stimulate the generation of ROS, including superoxide radicals and hydrogen peroxide [82]. These reactive species induce oxidative damage to lipids, proteins, and nucleic acids [91]. Lipid peroxidation results in the formation of malondialdehyde (MDA), a widely recognized biomarker of oxidative injury [83]. Elevated MDA levels have been consistently observed in occupationally exposed populations [92]. Concurrently, antioxidant defense systems such as superoxide dismutase and catalase become depleted under sustained oxidative pressure [84].
Oxidative imbalance triggers inflammatory signaling pathways across multiple tissues [93]. ROS activate immune responses that promote the release of inflammatory mediators, including cytokines and nitric oxide [85]. Increased nitric oxide levels have been documented in experimental exposure models, indicating activation of inflammatory cascades in organs such as the liver and kidneys [94]. These inflammatory processes contribute to progressive tissue damage, fibrosis, and organ dysfunction [86]. Elevated systemic inflammatory markers such as C-reactive protein have also been reported among exposed workers [95]. Persistent oxidative stress and inflammation are therefore key drivers of chronic multisystem diseases affecting the liver, lungs, kidneys, and cardiovascular system [87]. These findings establish oxidative stress as a central mechanism underlying cement dust toxicity [96- 100].
Toxicological Impact of Heavy Metals
Heavy metals present in cement dust significantly contribute to its overall toxicological burden on human health [61]. Commonly detected metals include chromium, cadmium, lead, cobalt, and nickel, all of which can accumulate in biological tissues following prolonged exposure [97]. Among these, hexavalent chromium is particularly hazardous due to its strong oxidative potential and ability to cross biological membranes [62]. Once internalized, chromium compounds interact with proteins and nucleic acids, disrupting cellular integrity and metabolic functions [98]. Toxicological evidence links chromium exposure to genetic mutations, DNA damage, and chromosomal abnormalities, increasing carcinogenic risk [63].
Beyond its carcinogenic potential, chromium also exerts immunotoxic effects [99]. Chronic exposure to heavy metals alters immune cell activity, including that of neutrophils and lymphocytes, thereby weakening host defense mechanisms [64]. Studies have reported reduced phagocytic activity of neutrophils in individuals exposed to metal-rich cement dust [100]. This immunosuppression increases susceptibility to infections and inflammatory diseases [65]. Additionally, accumulation of heavy metals in organs such as the kidneys and liver contributes to long-term toxicity, including hepatic injury and renal dysfunction [66]. These mechanisms highlight the severe health risks associated with occupational cement exposure and reinforce the need for strict workplace safety regulations [68].
Artificial Intelligence Applications in Occupational Health Monitoring
Artificial Intelligence (AI) has emerged as a transformative technology in occupational health by enabling real-time monitoring, predictive analytics, and intelligent decision-making across industrial environments. The increasing availability of large occupational datasets has facilitated the application of AI algorithms for detecting workplace hazards and assessing worker health status [24]. Machine learning techniques have demonstrated substantial potential in identifying complex relationships between environmental exposures and adverse health outcomes that may not be detected through conventional statistical approaches [31]. Recent advances in computational power have enabled the development of sophisticated predictive models capable of processing multidimensional occupational health datasets with high accuracy [45]. AI-based systems have been increasingly adopted in industries characterized by hazardous working conditions, including mining, manufacturing, chemical processing, and construction sectors [58].
Occupational health researchers have reported that intelligent monitoring systems can improve hazard detection rates while simultaneously reducing the burden of manual workplace inspections [67]. The integration of AI with sensor technologies has enabled continuous collection and analysis of environmental and physiological parameters in real-world occupational settings [72]. Furthermore, digital health platforms have facilitated the development of worker-centered surveillance systems capable of generating personalized health risk assessments [83]. AI technologies have also contributed to improved allocation of occupational health resources by identifying workers at elevated risk of disease development [94]. These technological developments have accelerated the transition from reactive occupational healthcare toward predictive and preventive occupational health management strategies [101]. Consequently, AI is increasingly recognized as a critical component of modern occupational health frameworks designed to enhance worker safety and long-term well-being.
AI-Based Exposure Assessment
Accurate exposure assessment remains a fundamental requirement for effective occupational health surveillance and risk management. Traditional exposure assessment methods often rely on periodic measurements and retrospective evaluations that may not adequately capture fluctuations in workplace hazards [36]. AI-driven exposure assessment systems have been developed to analyze data streams generated from environmental sensors, wearable devices, and workplace monitoring networks [49]. These systems can continuously evaluate airborne particulate concentrations, toxic gas levels, temperature variations, and worker movement patterns within industrial environments [54]. Machine learning algorithms have demonstrated considerable capability in identifying exposure hotspots and predicting high-risk activities associated with occupational hazards [61]. Advanced predictive models can integrate historical exposure records with real-time environmental measurements to estimate cumulative exposure burdens among workers [73].
Recent studies have reported that AI-assisted exposure assessment approaches outperform conventional monitoring techniques in terms of sensitivity, temporal resolution, and predictive accuracy [81]. Furthermore, intelligent monitoring systems can generate individualized exposure profiles that account for task-specific activities and worker behavior patterns [88]. The incorporation of geospatial analytics and Internet of Things technologies has further enhanced the precision of exposure mapping across complex occupational environments [97]. AIbased exposure assessment has therefore become an increasingly valuable tool for improving workplace safety and supporting evidence-based occupational health interventions [102].
Several occupational case studies have demonstrated the practical utility of AI-assisted exposure monitoring systems in industrial settings (Table 4). A large-scale occupational monitoring program conducted in manufacturing facilities employed machine learning algorithms to analyze airborne particulate data and successfully identified previously unrecognized exposure clusters [63]. Another case study involving construction workers utilized wearable sensors integrated with artificial neural networks to monitor worker proximity to dust-generating activities in real time [74]. The implementation of this system resulted in improved identification of hazardous work zones and facilitated timely intervention by occupational safety personnel [85]. Similar approaches have been applied in mining operations where predictive algorithms were used to estimate worker exposure to respirable particulate matter based on environmental and operational variables [93].
Researchers have also reported successful application of AIbased monitoring platforms for evaluating chemical exposure patterns among workers employed in heavy industrial processes [110]. In another investigation, deep learning models processed large datasets obtained from multiple environmental monitoring stations and accurately predicted future exposure trends under varying workplace conditions [111]. These findings collectively indicate that AI technologies can substantially improve the effectiveness of occupational exposure assessment programs [105]. Such advancements may be particularly beneficial for construction workers who experience frequent exposure to cement dust, heavy metals, and highly alkaline materials.
Machine Learning for Disease Risk Prediction
Machine learning has become one of the most extensively utilized AI methodologies for predicting occupational diseases and identifying vulnerable worker populations. The ability of machine learning algorithms to process large volumes of heterogeneous data has enabled the development of highly accurate disease prediction models [28]. Occupational health researchers have increasingly employed Random Forest, Support Vector Machine, Gradient Boosting, and Deep Neural Network algorithms to investigate disease susceptibility among exposed workers [43]. These models can simultaneously evaluate demographic variables, occupational histories, environmental exposures, lifestyle characteristics, and biological markers [57].
Machine learning approaches have demonstrated superior predictive performance compared with traditional regressionbased methods in several occupational health applications [69]. The capability of these algorithms to identify nonlinear interactions among risk factors has contributed significantly to improved disease forecasting accuracy [77]. Recent investigations have highlighted the value of predictive analytics for detecting early signs of occupational illness before clinical symptoms become apparent [89]. Such approaches facilitate targeted preventive interventions and support the implementation of personalized occupational health programs [95]. Furthermore, risk prediction models can assist employers and healthcare providers in prioritizing surveillance activities for high-risk worker populations [112]. Consequently, machine learning is increasingly viewed as a cornerstone technology for precision occupational health management [107].
Case studies from diverse occupational environments have demonstrated the effectiveness of machine learning-based disease prediction systems (Table 4). A cohort study involving industrial workers developed predictive models for respiratory dysfunction using occupational exposure histories and pulmonary function parameters [41]. The resulting algorithm achieved substantially greater predictive accuracy than conventional epidemiological approaches [52]. Another investigation utilized machine learning techniques to identify workers at increased risk of chronic inflammatory disorders based on biomarker profiles and workplace exposure records [66].
Table 4:Representative case studies of Artificial Intelligence Applications in occupational health monitoring.
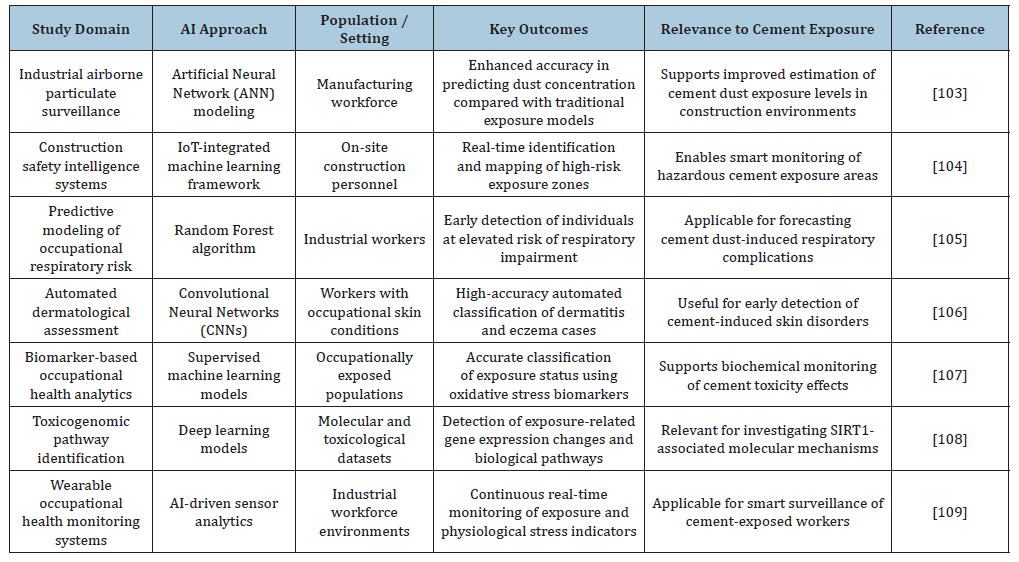
Researchers reported that predictive models successfully classified high-risk individuals several years before clinical diagnosis [79]. In an occupational dermatology study, machine learning algorithms were applied to identify workers susceptible to allergic contact dermatitis resulting from exposure to sensitizing chemicals [87]. Similar predictive frameworks have been proposed for construction workers exposed to cement dust and chromiumcontaining materials [98]. Deep learning models have also been employed to estimate disease progression trajectories among workers suffering from chronic occupational illnesses [113]. These findings illustrate the growing importance of predictive analytics in reducing occupational disease burden and improving worker health outcomes [114]. Such technologies have considerable potential for supporting proactive health management within the construction industry.
Computer Vision for Dermatological Screening
Computer vision has become an increasingly important component of AI-driven healthcare systems due to its ability to analyze medical images and identify pathological conditions with high precision. Occupational dermatology represents a particularly promising application area because many work-related skin disorders exhibit visible clinical manifestations [33]. Construction workers exposed to cement frequently develop dermatological conditions such as irritant contact dermatitis, allergic contact dermatitis, chemical burns, fissures, and chronic eczema [47]. Conventional diagnosis relies primarily on visual assessment by healthcare professionals and may be influenced by observer variability and limited access to specialist services [56].
Deep learning architectures, particularly Convolutional Neural Networks, have demonstrated remarkable performance in image classification and disease detection tasks [71]. These algorithms can automatically extract relevant visual features from dermatological images and distinguish between different skin disorders [82]. Recent technological developments have enabled deployment of computer vision systems through smartphones, tablets, and portable diagnostic devices [91]. Such innovations facilitate remote screening and continuous monitoring of occupational skin diseases in resource-limited environments [115]. AI-assisted dermatological assessment therefore offers significant opportunities for improving early diagnosis and treatment outcomes among exposed workers [111]. Computer vision technologies are expected to play an increasingly important role in future occupational health surveillance systems.
Several notable case studies have highlighted the effectiveness of computer vision approaches in dermatological screening applications. A large-scale dermatology project employed deep neural networks trained on thousands of clinical images and achieved diagnostic performance comparable to experienced dermatologists [39]. Another study developed a smartphone-based screening application capable of identifying inflammatory skin disorders from photographs obtained in non-clinical settings [53]. Researchers reported high classification accuracy for conditions including eczema, dermatitis, and allergic skin reactions [65].
Occupational health investigators have also explored the use of image analysis algorithms for monitoring skin abnormalities among workers exposed to industrial chemicals and environmental contaminants [76]. In one workplace surveillance program, AI-assisted image processing enabled early detection of skin lesions that had not yet been recognized through routine clinical examinations [84]. Similar methodologies could be applied to construction workers who regularly experience dermal exposure to wet cement and abrasive construction materials [96]. The integration of computer vision with occupational health databases may further enhance disease tracking and intervention planning [116]. These advances suggest that AI-powered dermatological screening has substantial potential for reducing the prevalence and severity of occupational skin diseases [113]. Such systems may ultimately contribute to improved worker quality of life and reduced healthcare expenditures.
AI-Assisted Biomarker and SIRT1 Analysis
The integration of AI technologies with biomarker research has opened new avenues for understanding occupational disease mechanisms and improving health surveillance strategies (Table 5). Occupational exposure to cement dust has been associated with oxidative stress, inflammation, cellular injury, and biochemical alterations affecting multiple organ systems [44]. Biomarkers such as malondialdehyde, superoxide dismutase, catalase, C-reactive protein, alanine aminotransferase, aspartate aminotransferase, creatinine, and urea have been widely investigated as indicators of toxicological responses [59]. AI algorithms can process large biomarker datasets and identify complex molecular patterns associated with occupational exposure and disease development [68].
Table 5:Applications of Artificial Intelligence in occupational health and cement exposure research.
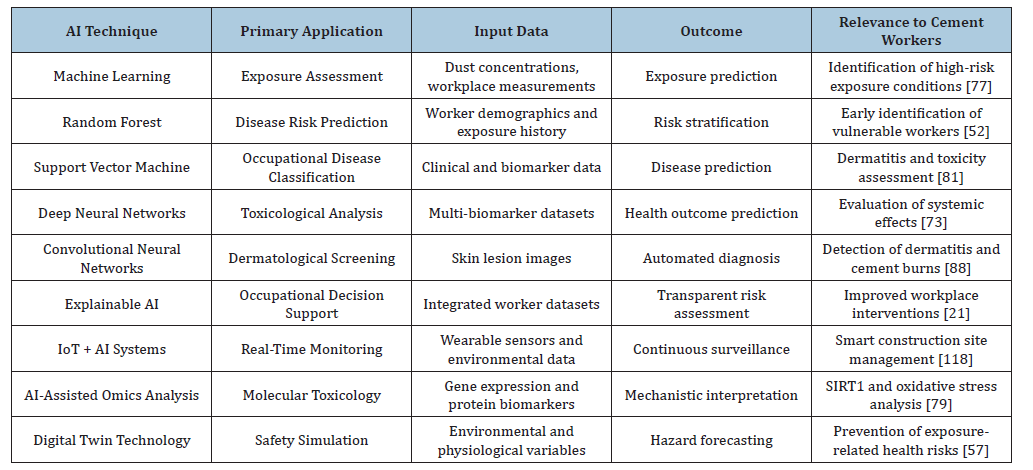
Machine learning models have demonstrated significant capability in predicting health outcomes based on multidimensional biological data [78]. Recent studies have shown that biomarkerbased predictive systems can improve early detection of occupational illnesses and facilitate personalized risk assessment [90]. The integration of molecular, clinical, and environmental information within AI frameworks has enhanced understanding of disease pathogenesis in exposed populations [117]. Furthermore, advanced computational approaches have enabled identification of previously unrecognized relationships between occupational hazards and biological responses [118]. These developments have strengthened the role of AI as a valuable tool for precision toxicology and occupational medicine [116]. AI-assisted biomarker analysis is therefore expected to become increasingly important in future occupational health monitoring programs.
Particular attention has recently been directed toward Sirtuin 1 (SIRT1), a NAD⁺-dependent regulatory protein involved in oxidative stress control, inflammation regulation, DNA repair, and cellular longevity. Experimental investigations have suggested that environmental toxicants and heavy metals may influence SIRT1 expression and activity through multiple molecular pathways [101]. Occupational exposure to chromium, cadmium, nickel, and other toxic elements present in cement dust has been associated with oxidative stress responses that may contribute to SIRT1 dysregulation [115]. Researchers have proposed that reduced SIRT1 activity may promote inflammatory signaling, mitochondrial dysfunction, and accelerated cellular aging [117].
AI-assisted molecular analysis platforms have demonstrated substantial capability in evaluating gene expression profiles and identifying biomarkers associated with occupational toxicity [110]. Machine learning models have successfully differentiated exposed and non-exposed populations based on integrated biomarker signatures that include oxidative stress indicators and regulatory proteins [119]. Several case studies have reported the successful application of deep learning approaches for identifying molecular pathways involved in chronic inflammatory diseases and toxicological responses [117]. Similar methodologies could be employed to investigate the mechanistic role of SIRT1 in cement-induced dermatological and systemic health effects [118]. The incorporation of SIRT1 within AI-enabled occupational health frameworks may facilitate early disease detection, risk stratification, and personalized intervention strategies [120]. Therefore, AI-assisted biomarker and SIRT1 analysis represent a promising research direction for advancing occupational health surveillance among construction workers exposed to cement and related environmental hazards.
SIRT1-Associated Molecular Effects of Cement Exposure
Sirtuin 1 (SIRT1), a NAD⁺-dependent deacetylase, plays a critical role in regulating cellular aging, oxidative stress responses, and metabolic stability, making it highly relevant in occupational toxicology [101]. Cement dust contains a complex mixture of xenobiotics, including alkaline compounds and trace heavy metals such as hexavalent chromium, which may interfere with intracellular signaling pathways and suppress SIRT1 activity [115]. Reduced SIRT1 function is associated with increased oxidative stress, impaired DNA repair capacity, and activation of inflammatory signaling, ultimately accelerating cellular aging and tissue degeneration [117]. In workers exposed to cement without adequate protection, these molecular disruptions may intensify both dermatological and systemic toxicity [103].
Moreover, the equilibrium between SIRT1 activation and inhibition is increasingly recognized as a key determinant of cellular resistance to environmental stressors [119]. A reduction in SIRT1 expression is linked to metabolic imbalance, hepatic dysfunction, and chronic inflammation, conditions frequently observed in cement-exposed populations [101]. Monitoring SIRT1 levels in biological samples may therefore serve as an early biomarker of cumulative occupational toxicity and disease progression [115]. Future research should focus on elucidating dose–response relationships between cement-related xenobiotics and SIRT1 regulation, as well as developing interventions aimed at restoring its protective cellular functions in high-risk workers [117].
AI in Occupational Health Monitoring: Implications and Future Directions
Prolonged exposure to cement, particularly among construction workers who handle materials without adequate protective gloves, remains a significant occupational health challenge supported by extensive epidemiological evidence [102]. Occupational skin disorders related to cement exposure are among the most commonly reported work-related conditions worldwide, with prevalence estimates suggesting that approximately 5-15% of construction workers develop dermatitis over the course of their careers, especially among masons and concrete handlers [113]. Clinical evaluations in hospital-based studies have reported that nearly 46% of examined construction workers suffer from occupational skin conditions, including contact dermatitis and callosities, with contact dermatitis accounting for roughly 20% of cases [112].
Continuous exposure to cement dust, which contains highly alkaline compounds and trace metals such as hexavalent chromium, can trigger a spectrum of dermatological conditions ranging from irritant reactions and allergic dermatitis to eczema, chemical burns, and ulcerative lesions in severe cases [116]. In addition to visible skin damage, occupational exposure studies increasingly demonstrate systemic biochemical alterations, including elevated oxidative stress markers such as malondialdehyde and reduced antioxidant defense capacity compared to unexposed populations, indicating underlying cellular injury [118]. These combined dermatological and systemic effects highlight cement dust as a complex occupational hazard with both immediate and long-term health consequences [111].
The integration of Artificial Intelligence (AI) into occupational health monitoring offers a transformative approach to addressing these risks by enabling early detection, predictive modeling, and continuous surveillance of exposure-related health outcomes [111]. Traditional preventive approaches rely heavily on periodic assessments and self-reported symptoms; however, AI-driven systems can analyze real-time data from wearable sensors, environmental monitoring devices, and clinical records to identify early signs of exposure-related pathology [117]. In particular, machine learning algorithms can be trained to recognize patterns associated with dermatological irritation, oxidative stress biomarkers, and exposure intensity, thereby improving early intervention strategies [114]. Furthermore, computer vision systems can assist in automated skin lesion detection among workers, enabling rapid screening for dermatitis, eczema, and chemical burns in occupational environments [119]. These technologies collectively enhance workplace safety frameworks by shifting occupational health management from reactive treatment to proactive prevention.
Future research in this domain should focus on expanding AI-integrated occupational health systems through large-scale longitudinal and mechanistic studies that combine dermatological, biochemical, and environmental datasets [108]. While existing research has established correlations between cement exposure and oxidative stress biomarkers, there remains a critical need for AI-enabled models that can accurately predict dose–response relationships, exposure timelines, and cumulative toxic effects in real-world construction settings [113]. Advanced AI methodologies, including deep learning and predictive analytics, may also support the development of safer construction materials by evaluating the toxicological profiles of innovative cement formulations and chromium-reduced alternatives [105]. In addition, integrating molecular data into AI systems may help identify key biological pathways affected by heavy metals and irritants, thereby supporting targeted intervention strategies to reduce cellular damage [120]. Finally, future occupational health frameworks must incorporate socio-economic and accessibility considerations, ensuring that AI-based monitoring systems, protective equipment, and training programs are equitably available across diverse construction environments to maximize public health impact [114].
Conclusion
Cement remains a chemically complex and widely utilized construction material that poses substantial occupational health risks, particularly for workers who are not adequately protected with gloves, clothing, and respiratory safeguards. Its highly alkaline nature, abrasive particulate structure, and presence of sensitizing heavy metals such as hexavalent chromium, cobalt, and nickel collectively contribute to a broad spectrum of dermatological disorders, including irritant and allergic contact dermatitis, chemical burns, eczema, and hyperkeratosis. Epidemiological evidence consistently shows that the hands, forearms, and lower limbs are the most frequently affected body regions, underscoring the occupational nature of exposure and the urgent need for improved workplace protection strategies.
Beyond cutaneous manifestations, cement dust exposure also produces significant biochemical and systemic effects. Inhalation, dermal absorption, or accidental ingestion of fine cement particles allows toxic constituents such as silicon oxide, aluminum oxide, chromium, cadmium, lead, and other heavy metals to accumulate in vital organs including the liver, kidneys, and lungs. This accumulation disrupts cellular homeostasis and promotes oxidative stress, characterized by increased lipid peroxidation, depletion of antioxidant enzymes such as superoxide dismutase (SOD) and catalase (CAT), and activation of inflammatory pathways. These processes are reflected in elevated biochemical markers such as liver enzymes, creatinine, urea, malondialdehyde, and C-reactive protein, confirming multi-organ involvement in exposed populations.
Traditional preventive strategies-including the use of personal protective equipment, workplace ventilation, hygiene protocols, and occupational health surveillance-remain essential for reducing exposure-related risks. However, their effectiveness is often limited by inconsistent implementation, particularly in low-resource and informal construction sectors. Emerging integration of Artificial Intelligence (AI) into occupational health monitoring offers a promising advancement by enabling real-time exposure tracking, predictive risk assessment, and early detection of dermatological and systemic abnormalities. AI-driven tools, combined with biomarker monitoring and digital health systems, have the potential to significantly strengthen preventive frameworks and shift occupational health management from reactive to predictive models.
Future research should prioritize longitudinal, mechanistic, and AI-integrated approaches to better understand the cumulative effects of cement exposure across dermatological, biochemical, and systemic levels. In particular, AI-based predictive modeling, wearable sensor technologies, and advanced data analytics can support early identification of high-risk exposure patterns and improve occupational safety interventions. Additionally, the development of safer cement formulations, including chromiumreduced and bioengineered alternatives, represents an important avenue for reducing inherent material toxicity. Socio-economic considerations, such as equitable access to AI-enabled monitoring systems, protective equipment, and occupational health services, must also be addressed to ensure inclusive implementation. Collectively, integrating technological innovation with regulatory frameworks and preventive occupational strategies is essential to safeguarding construction workers from the multi-systemic health impacts of cement exposure.
Funding Statement
Not Applicable
Conflict of Interest
Authors declare that they have no conflict of interest with this publication.
Acknowledgement
The authors would like to thank every person and department who helped throughout this research.
References
- Hedberg YS, Lidén C, Lindberg M (2016) Chromium dermatitis in a metal worker due to leather gloves and alkaline coolant. Acta Dermato-Venereologica 96(1): 104-105.
- Nijhawan RI, Molenda M, Zirwas MJ, Jacob SE (2009) Systemic contact dermatitis. Dermatologic Clinics 27(3): 355-364.
- Achmad RT, Auerkari EI (2017) Effects of chromium on human body. Annu Res Rev. Biol 13(3): 1-8.
- Bermudez GM, Moreno M, Invernizzi R, Plá R, Pignata ML (2010) Heavy metal pollution in topsoils near a cement plant: the role of organic matter and distance to the source to predict total and HCL-extracted heavy metal concentrations. Chemosphere 78(4): 375-381.
- Elhosary NA, Maklad E, Soliman N, El-Ashmawy, Oreby M (2014) Evaluation of oxidative stress and DNA damage in cement and tannery workers in Egypt. Inhal Toxicol 26(5): 289-298.
- Khatami AM, Nassiri-Kashani F, Gorouhi S, Babakoohi A, Kazerouni-Timsar, et al. (2013) Allergic contact dermatitis to metal allergens in Iran. Int J Dermatol 52(12): 1513-1518.
- Rycroft RJ (2001) Textbook of contact dermatitis. Springer, Berlin, Germany.
- Thyssen JP, Ross-Hansen K, Menné T, Johansen JD (2010) Patch test reactivity to metal allergens following regulatory interventions: a 33-year retrospective study. Contact Dermatitis 63(2): 102-106.
- Wong CC, Gamboni SE, Palmer AM, Nixon RL (2015) Occupational allergic contact dermatitis to chromium from cement: estimating the size of the problem in Australia. Australas J Dermatol 56(4): 290-293.
- Kowalik T, Logoń D, Maj M, Rybak J, Ubysz A (2019) Chemical hazards in construction industry. E3S Web of Conferences 97: 03032.
- Bedoya-Marrugo EA, Severiche-Sierra CA, Sierra-Calderon DD, Jaimes-Morales J, Marrugo-Ligardo YA, et al. (2017) Conditions of work and dermatitis in workers exposed to chemical risks by cement. International Journal of Applied Engineering Research 12(22): 12119-12126.
- Chou TC, Wang PC, Wu JD, Sheu SC (2016) Chromium-induced skin damage among Taiwanese cement workers. Toxicol Ind Health 32(10): 1745-1751.
- Saji KG, Zubair M, Varghese PR (2014) Health risk in workers exposed to wet cement. Int J Res 4(5): 2307-2083.
- Nunes RAA, De Alencar DB, Bezerra CMVO, Bezerra IFO (2019) Health damage to civil construction workers due to use and exposure to cement. ITEGAM-JETIA 5(20): 116-120.
- Shanshal SA, Al-Qazaz H (2022) The impact of exposure to cement dust on the parameters of oxidative stress among cement plant workers. GJPHM 4(1).
- Abdel-Hamid IA, Agha SA, Moustafa YM, El-Labban AM (2003) Pityriasis Amiantacea: A clinical and etiopathologic study of 85 patients. Int J Dermatol 42(4): 260-264.
- Afridi HI, Brabazon D, Kazi TG, Naher S, Nesterenko E (2011) Evaluation of essential trace and toxic elements in scalp hair samples of smokers and alcohol user hypertensive patients. Biol Trace Elem Res 143(3): 1349-1366.
- Ala SM, Shokrzadeh M, Golpour M, Salehifar E, Alami M, et al. (2013) Zinc and copper levels in Iranian patients with psoriasis: a case control study. Biological Trace Element Research 153 (2013): 22-27.
- Arora PN, Dhillon KS, Rajan SR, Sayal SK, Das AL (2002) Serum zinc levels in cutaneous disorders. Med J Armed Forces India 58(4): 304-306.
- Basavaraj K, Darshan M, Shanmugavelu P, Rashmi R, Mhatre AY, et al. (2009) Study on the levels of trace elements in mild and severe psoriasis. Clinica Chimica Acta 405(1-2): 66-70.
- Brown KM, Arthur JR (2001) Selenium, selenoproteins human health: a review. Public Health Nutrition 4: 593-599.
- Chen W, Zhou X, Zhu W (2019) Trace elements homeostatic imbalance in psoriasis: a meta-analysis. Biological Trace Element Research 191: 313-322.
- Elder JT, Nair RP, Henseler T, Jenisch S, Stuart P, et al. (2001) The genetics of psoriasis 2001: the odyssey continues. Archives of Dermatology 137(11): 1447-1454.
- Gelfand JM, Weinstein R, Porter SB, Neimann AL, Berlin JA, et al. (2005) Prevalence and treatment of psoriasis in the United Kingdom: a population-based study. Archives of Dermatology 141(12): 1537-1541.
- Ginarte M, Pereiro M, Fernandez-Redondo V, Toribio J (2000) Pityriasis amiantacea as manifestation of tinea capitis due to microsporum canis. Mycoses 43(1-2): 93-96.
- Hanel KH, Cornelissen C, Luscher B, Baron JM (2013) Cytokines and the skin barrier. Int J Mol Sci 14(4): 6720-6745.
- Kim JE, Yoo SR, Jeong MG, Ko JY, Ro YS (2014) Hair zinc levels and the efficacy of oral zinc supplementation in children with atopic dermatitis. Acta Dermato-Venereologica 94(5): 558-562.
- Kolachi NF, Kazi TG, Baig JA, Kandhro GA, Khan S, et al. (2010) Microwave assisted acid extraction of se from medicinal plants followed by electrothermal atomic absorption spectrometric determination. AOAC International 93(2): 694-702.
- Kolachi NF, Kazi TG, Afridi HI, Kazi N, Kandhro GA, et al. (2011) Distribution of copper, iron and zinc in biological samples (scalp hair, serum, blood and urine) of Pakistani viral hepatitis (A-E) patients and controls. Biol Trace Elem Res 143(1): 116-130.
- Winder C, Carmody M (2002) The dermal toxicity of cement. Toxicol Ind Health 18(7): 321-331.
- Rauf AU, Mallongi A, Astuti RDP (2020) Heavy metal contributions on human skin disease near cement plant: A systematic review. Open Access Macedonian Journal of Medical Sciences 8(F): 117-122.
- Afridi HI, Kazi TG, Kazi N, Kandhro GA, Baig JA, et al. (2011) Evaluation of cadmium, chromium, nickel, and zinc in biological samples of psoriasis patients living in Pakistani cement factory area. Biological Trace Element Research 142(3): 284-301.
- Koh DH, Kim TW, Jang SH, Ryu HW (2011) Cancer mortality and incidence in cement industry workers in Korea. Saf Health Work 2(3): 243-249.
- Lushniak BD (2004) Occupational contact dermatitis. Dermatologic Therapy 17(3): 272-277.
- Cha KT, Oh SS, Yoon JH, Lee KH, Kim SK, et al. (2011) Adverse health outcomes in residents exposed to cement dust. Toxicology and Environmental Health Sciences 3(4): 239-244.
- Thyssen JP, Jensen P, Carlsen BC, Engkilde K, Menné T, et al. (2009) The prevalence of chromium allergy in Denmark is currently increasing as a result of leather exposure. Br J Dermatol 161(6): 1288-1293.
- Sigvardsen NM, Ottosen LM (2019) Characterization of coal bio ash from wood pellets and low-alkali coal fly ash and use as partial cement replacement in mortar. Cement and Concrete Composites 95: 25-32.
- Aljeesh Y, Al Madhoun W, El Jabaly S (2015) Effect of exposure to cement dust on pulmonary function among cement plants workers in the middle governorate, Gaza, Palestine. Public Health Research 5(5): 129-134.
- Spiro J (2008) Occupational skin diseases. Principles and Practice of Skin Toxicology 27(4): 259-277.
- Normohammadi M, Kakooei H, Omidi L, Yari S, Alimi R (2016) Risk assessment of exposure to silica dust in building demolition sites. Saf Health Work 7(3): 251-255.
- Mallongi A, Stang, Syamsuar M, Fajar MN, Pujiastuti RD, et al. (2019) Risks assessment of silica contamination on the communities living surround the cement industry, Pangkep Indonesia. Indian Journal of Public Health Medical Research 10(10): 1619.
- Omrani MA, Modarres A (2018) Emulsified cold recycled mixtures using cement kiln dust and coal waste ash-mechanical and environmental impacts. J Clean Prod 199: 101-111.
- Thomas B, Kulichova D, Wolf R, Summer B, Mahler V, et al. (2015) High frequency of contact allergy to implant and bone cement components, in particular gentamicin, in cemented arthroplasty with complications: Usefulness of late patch test reading. Contact Dermatitis 73(6): 343-349.
- Stern AH, Bagdon RE, Hazen RE, Marzulli FN (1993) Risk assessment of the allergic dermatitis potential of environmental exposure to hexavalent chromium. J Toxicol Environ Health 40(4): 613-641.
- Lin PH, Matthew S, Li H, Lee PHU, Steinberg SM, et al. (2018) Zinc in wound healing modulation. Nutrients 10(1): 16.
- McKenzie RC (2000) Selenium, ultraviolet radiation and the skin. Clinical and Experimental Dermatology 25(8): 631-636.
- Mohamad NS (2013) Trace elements homeostatic imbalance in mild and severe psoriasis: a new insight in biomarker diagnostic value for psoriasis. Our Dermatol Online 4(4): 449-452.
- Naziroglu M, Yildiz K, Tamturk B, Erturan I, Flores-Arce M (2012) Selenium and psoriasis. Biol Trace Elem Res 150: 3-9.
- Park K (2015) Role of micronutrients in skin health and function. Biomolecules & Therapeutics 23(3): 207-217.
- Pisoschi AM, Pop A (2015) The role of antioxidants in the chemistry of oxidative stress: a review. Eur J Med Chem 97: 55-74.
- Rayman MP (2008) Food-chain selenium and human health: emphasis on intake. Br J Nutr 100(2): 254-268.
- Rayman MP (2012) Selenium and human health. Lancet 379(9822): 1256-1268.
- Rostan EF, DeBuys HV, Madey DL, Pinnell SR (2002) Evidence supporting zinc as an important antioxidant for skin. Int J Dermatol 41(9): 606-611.
- Salgueiro MJ, Zubillaga M, Lysionek A, Sarabia MI, Caro R, et al. (2005) Zinc as an essential micronutrient: A review. Nutrition Research 20(5): 737-755.
- Samejo S, Kazi AG, Afridi HI, Kazi TG (2019) Evaluate the effect of cadmium on levels of zinc in scalp hair and blood samples of smoker and nonsmoker psoriatic patients at different stage. Environ Sci Pollut Res Int 26(31): 31763-31769.
- Schwart JR, Marsh RG, Draelos ZD (2005) Zinc and skin health: Overview of physiology and pharmacology. Dermatol Surg 31(7 Pt 2): 837-847.
- Serwin AB, Wasowicz W, Gromadzinska J, Chodynicka B (2003) Selenium status in psoriasis and its relations to the duration and severity of the disease. Nutrition 19(4): 301-304.
- Shahidi DM, Namazi N, Khalilazar S, Younespour S (2012) Trace elements status in psoriasis and their relationship with the severity of the disease. Iran J Dermatol 15(2): 38-41.
- Shahrad MB, Behnam SE, Koo JY (2005) Smoking and psoriasis. Skinmed 4(3): 174-176.
- Stehbens WE (2003) Oxidative stress, toxic hepatitis, and antioxidants with particular emphasis on zinc. Experimental and Molecular Pathology 75(3): 265-276.
- Stewart MS, Spallholz JE, Neldner KH, Pence BC (1999) Selenium compounds have disparate abilities to impose oxidative stress and induce apoptosis. Free Radic Biol Med 26(1-2): 42-48.
- Tisma VS, Basta-Juzbasic A, Jaganjac M, Brcic L, Dobric I, et al. (2009) Oxidative stress and ferritin expression in the skin of patients with Rosacea. Journal of the American Academy of Dermatology 60(2): 270-276.
- Trouba KJ, Hamadeh HK, Amin RP, Germolec DR (2002) Oxidative stress and its role in skin disease. Antioxid Redox Signal 4(4): 665-673.
- Verardino GC, Azulay-Abulafia L, de Macedo PM, Jeunon T (2012) Pityriasis Amiantacea: Clinical-dermatoscopic features and microscopy of hair tufts. An Bras Dermatol 87(1): 142-145.
- Wolff K, Goldsmith LA, Katz SI, Gilcherest BA, Paller AS, et al. (2008) Fitzpatrick’s dermatology in general medicine. (7th edn), McGraw-Hill Medical, New York, USA.
- Yang L, Wang W, Hou S, Peterson PJ, Williams WP (2002) Effects of selenium supplementation on Arsenism: an intervention trial in inner Mongolia. Environmental Geochemistry and Health 24: 359-374.
- Yildirim M, Inaloz HS, Baysal V, Delibas N (2003) The role of oxidants and antioxidants in psoriasis. J Eur Acad Dermatol Venereol 17(1): 34-36.
- Zhou Q, Mrowietz U, Yazdi MR (2009) Oxidative stress in the pathogenesis of psoriasis. Free Radic Biol Med 47(7): 891-905.
- Zoidis E, Seremelis I, Kontopoulos N, Danezis GP (2018) Selenium-dependent antioxidant enzymes: Actions and properties of selenoproteins. Antioxidants 7(5): 66.
- Kridin K, Bergman R, Khamaisi M, Zelber-Sagi S, Weltfriend S (2016) Cement-Induced chromate occupational allergic contact dermatitis. Dermatitis 27(4): 208-214.
- Saji KG, Zubair M, Nair SB, Varghese PR (2018) An epidemiological study on effect of occupational exposure of cement. Int J Community Med Public Health 5(12): 5105-5109.
- Kazi AG, Afridi HI, Arain MB, Kazi TG (2021) Adverse impact of occupational exposure on laborers of cement industry have scalp psoriasis and pityriasis amiantacea with deficiency of zinc and selenium: impact of mineral supplement. Environ Sci Pollut Res Int 28(48): 68330-68337.
- Abrams K, Harvell JD, Shriner, P Wertz, H Maibach, et al. (1993) Effect of organic solvents on in vitro human skin water barrier function. Journal of Investigative Dermatology 101(4): 609-613.
- American Conference of Governmental Industrial Hygienists (ACGIH) (2005) Threshold limit values for chemical substances and physical agents and biological exposure indices. ACGIH, Cincinnati, USA.
- Avnstorp C (1992) Cement Eczema: An epidemiological intervention study. Acta Derm Venereol Suppl (Stockh) 179: 1-22.
- Brown CP, Spivey GH, Valentine JL, Browdy BL (1980) Cigarette smoking and lead levels in occupationally exposed lead workers. J Toxicol Environ Health 6(4): 877-883.
- Bock M, Schmidt A, Bruckner T, Diepgen TL (2003) Occupational skin disease in the construction industry. Br J Dermatol 149(6): 1165-1171.
- Boyd AS, Stasko T, King LE Jr, Cameron GS, Pearse AD (1999) Cigarette smoking-associated elastotic changes in the skin. J Am Acad Dermatol 41(1): 23-26.
- Chen CJ, Shih TS, Chang HY, Yu HS, Wu JD, et al. (2008) The total body burden of chromium associated with skin disease and smoking among cement workers. Science of the Total Environment 391(1): 76-81.
- Chou TC, Shih TS, Sheu HM, Chang SJ, Huang CC, et al. (2004) The effect of personal factors on the relationship between carbon disulfide exposure and urinary 2-Thiothiazolidine-4-Carboxylic Acid Levels in rayon manufacturing workers. Science of the Total Environment 322(1-3): 51-62.
- Chou TC, Shih TS, Tsai JC, Wu JD, Sheu HM, et al. (2004) Effect of occupational exposure to rayon manufacturing chemicals on skin barrier to evaporative water loss. J Occup Health 46(5): 410-417.
- Chou TC, Chang HY, Chen CJ, Yu HS, Wu JD, et al. (2008) Effect of hand dermatitis on the total body burden of chromium after ferrous sulfate application in cement among cement workers. Contact Dermatitis 59(3): 151-156.
- Alabi OA, Ayeni FE, Afolabi TA (2025) Health risk assessment of toxic metals and DNA damage in somatic and germ cells by soil and groundwater of a major cement factory in Nigeria. Toxicological Sciences 203(2): 227-241.
- Islam MM, Akhter S, Khanam S, Nasrin T, Gupta AD, et al. (2025) Effect of cement pollution on serum creatinine and blood urea in cement factory workers. Chattagram Maa-O-Shishu Hospital Medical College Journal 24(2): 86-90.
- Helen OA, B Temilade TA, Olwapelumi OE, Ebun AB, Olatunbosun AF, et al. (2025) Effects of cement dust exposure on liver function among construction workers in akala express. International Research Journal of Gastroenterology and Hepatology 8(1): 28-39.
- Ahmad R, Haque M, Abira M, Akhter QS (2026) Hepatic effects of chronic occupational cement dust exposure: Enzyme profile analysis. Bangladesh Journal of Medical Science 25(1): 91-102.
- Piemonte ED, Panico R, Gilligan GM, Lazos JP (2026) Effects of chronic sun exposure on the labial mucosa. In Lifestyle in Oral Health and Disease: A comprehensive guide for oral healthcare providers, Springer Nature, Cham, Switzerland, pp. 293-327.
- Aulia NS, Charisma N, Laoli VTE, Nasirah T, Salsabila AP, et al. (2026) Risk control of exposure to hazardous chemicals in the workplace. In International Conference of Public Health, pp. 352-362.
- McKay RL, Wu S (2026) Blue light and ultraviolet radiation: Comparative biophysical properties and their roles in skin carcinogenesis and photoaging. Journal of Dermato-Oncology 2(1): 2595383.
- Liao Z, Parumasivam T, Xiao Z, Zhu X, Yeoh YK, et al. (2026) Emerging therapeutic and cosmeceutical applications of phenylalanine and its metabolites. Cutan Ocul Toxicol 45(1): 127-144.
- Chuong CM, Nickoloff BJ, Elias PM, Goldsmith LA, Macher E, et al. (2002) What is the ‘true’ function of skin? Exp Dermatol 11(2): 159-187.
- Elias PM (2005) Stratum corneum defensive functions: an integrated view. J Invest Dermatol 125(2): 183-200.
- Ernster VL, Grady D, Miike R, Black D, Selby J, et al. (1995) Facial wrinkling in men and women, by smoking status. Am J Public Health 85(1): 78-82.
- Fowler JF, Kauffman CL, Marks JG, Proctor DM, Fredrick MM, et al. (1999) An environmental hazard assessment of low-level dermal exposure to hexavalent chromium in solution among chromium-sensitized volunteers. J Occup Environ Med 41(3): 150-160.
- Freiman A, Bird G, Metelitsa AI, Barankin B, Lauzon GJ, et al. (2004) Cutaneous effects of smoking. J Cutan Med Surg 8(6): 415-423.
- Gammelgaard B, Fullerton A, Avnstorp C, Menné T (1992) Permeation of chromium salts through human skin in vitro. Contact Dermatitis 27(5): 302-310.
- Hui X, Elkeeb R, Chan H, Maibach HI (2012) Ability to estimate relative percutaneous penetration via surrogate marker-transepidermal water loss? Skin Res Technol 18(1): 108-113.
- Machado M, Salgado TM, Hadgraft J, Lane ME (2010) The relationship between transepidermal water loss and skin permeability. Int J Pharm 384(1-2): 73-77.
- Morita A (2007) Tobacco smoke causes premature skin aging. J Dermatol Sci 48(3): 169-175.
- Pflücker F, Wendel V, Hohenberg H, Gärtner E, T Will, et al. (2001) The human stratum corneum layer: an effective barrier against dermal uptake of different forms of topically applied micronised titanium dioxide. Skin Pharmacol Appl Skin Physiol 14(Suppl 1): 92-97.
- Pinnagoda J, Tupker RA (1995) Measurement of the transepidermal water loss. In: Serup, et al. (Eds.), Handbook of Non-Invasive Methods and the Skin, CRC Press, Florida, USA, pp. 173-178.
- Stern AH, Bagdon RE, Hazen RE, Marzulli FN (1993) Risk assessment of the allergic dermatitis potential of environmental exposure to hexavalent chromium. Journal of Toxicology and Environmental Health 40(4): 613-641.
- She P, Mo F, Zhu P, Zhong TP (2026) Regulation of mitochondrial biogenesis and energy metabolism in the heart.
Chin Med J 139(7): 1008-1097. - Zhang C, Sun R, Jiang Q (2026) Establishment and research progress of animal models for intervertebral disc degeneration. Open Life Sci 21(1): 20251295.
- Ulenbelt P, Lumens ME, Géron HM, Herber RF, Broersen S, et al. (1990) Work hygienic behaviour as modifier of the lead air-lead blood relation. Int Arch Occup Environ Health 62(3): 203-207.
- Wang B, Wu JD, Sheu SC, Shih TS, Chang HY, et al. (2011) Occupational hand dermatitis among cement workers in Taiwan. Journal of the Formosan Medical Association 110(12): 775-779.
- Wen CP, Levy DT, Cheng TY, Hsu C, Tsai S (2005) Smoking behaviour in Taiwan, 2001. Tobacco Control 14(Suppl 1): I51-I55.
- Yosipovitch G, Xiong GL, Haus E, Sackett-Lundeen L, Ashkenazi I, et al. (1998) Time-Dependent variations of the skin barrier function in humans: Transepidermal water loss, stratum corneum hydration, skin surface pH, and skin temperature. Journal of Investigative Dermatology 110(1): 20-23.
- Zhai H, Leow YH, Maibach HI (1998) Human barrier recovery after acute acetone perturbation: An irritant dermatitis model. Clin Exp Dermatol 23(1): 11-13.
- Rubio L, Alonso C, Lopez O, Gelen Rodríguez, Luisa Coderch, et al. (2011) Barrier function of intact and impaired skin: Percutaneous penetration of caffeine and salicylic acid. Int J Dermatol 50(7): 881-889.
- Wang J, Lin J, Liu L, Liu S, Xie Z, et al. (2026) Ciprofol promotes SIRT1-mediated Raf regulation of ERK1/2 hyperphosphorylation. Neurochem Res 51(1): 62.
- Tsai JC, Sheu HM, Hung PL, Cheng CL (2001b) Effect of barrier disruption by acetone treatment on the permeability of compounds with various lipophilicities: implications for the permeability of compromised skin. J Pharm Sci 90(9): 1242-1254.
- Tsai JC, Hung PL, Sheu HM, Cheng CL (2001a) Molecular weight dependence of polyethylene glycol penetration across acetone-disrupted permeability barrier. Arch Dermatol Res 293(6): 302-307.
- Magnano GC, Malard V, Crosera M, Marussi G, Debellemanière O (2025) Evaluation of metal removal from skin exposed to stainless steel and cement particles: Insights from an in vitro permeation study. Toxicol In Vitro 111: 106173.
- Rougier A, Dupuis D, Lotte C, Roguet R, Wester RC, et al. (1986) Regional variation in percutaneous absorption in man: measurement by the stripping method. Arch Dermatol Res 278(6): 465-469.
- Zhou Q, Chen W, Gu C, Liu H, Hu X, et al. (2023) Selenium-modified bone cement promotes osteoporotic bone defect repair in ovariectomized rats by restoring GPx1-mediated mitochondrial antioxidant functions. Regen Biomater 10: rbad011.
- Roberts MS, Walters KA (1998) The relationship between structure and barrier function of skin. In: Roberts MS & Walters KA (Eds.), Dermal Absorption and Toxicity Assessment, Marcel Dekker, New York, USA, pp. 1-42.
- Li Y, Zhang W, Cai Y, Yang D (2025) Ginsenoside Rb2 inhibits the pyroptosis in myocardial ischemia progression through regulating the SIRT1-Mediated Deacetylation of ASC. Biochem Genet 63(3): 2623-2637.
- Shelnutt SR, Goad P (2007) Dermatological toxicity of hexavalent chromium. Critical Reviews in Toxicology 37(5): 375-387.
- Keram SP, Deshmukh GD (2025) Bioaccumulation of trace elements exposed to pollution from UltraTech cement factory area near Gadchandur, Maharashtra, India. Biochem Cell Arch 25(2).
© 2026 Zeenat Khan. This is an open access article distributed under the terms of the Creative Commons Attribution License , which permits unrestricted use, distribution, and build upon your work non-commercially.
Editor In Chief







.jpg)






























Signup for Newsletter

Quick Links
 Editorial Board Registrations
 Submit your Article
 Best Paper of the Volume
 Reprints
 Refer a Friend
 Advertise With Us
Our Recent Edition





Top Editors




.jpg)

















.bmp)
.jpg)
.png)
.jpg)













.jpg)






.png)

.png)




.png)




Financial Support

Sponsors

Latest e-Books

Latest Video
 a Creative Commons Attribution 4.0 International License. Based on a work at www.crimsonpublishers.com.
Best viewed in

 | Above IE 9.0 version